Hip Arthritis
What hip osteoarthritis is, the non-surgical options worth trying, and how to know when a replacement conversation makes sense.

The short answer
Hip arthritis is the gradual loss of the smooth cartilage that lets the ball-and-socket joint glide. It can cause groin pain, stiffness, and a shrinking walking range. Treatment starts with non-surgical care; replacement becomes a conversation when meaningful pain or lost function persists despite that care.
What is actually happening in the joint
Cartilage does not show on an X-ray, but the space it occupies does. As cartilage thins, the joint space narrows, bone begins to bear load it was never meant to carry, and the body responds with stiffness, bone spurs, and inflammation. When the space is nearly gone, that is the finding people are told is “bone-on-bone”: a description of advanced osteoarthritis on the X-ray, not a decision about treatment.
Symptoms rarely march in a straight line. Many people have good weeks and bad ones. The useful measure is the trend across months: what has walking, sleep, work, or recreation lost?
What can help before any operation
Reasonable non-surgical care can include activity modification, targeted strengthening and physical therapy, weight management where it applies, anti-inflammatory medication when appropriate for your health, and selected injections. Many people gain meaningful time with these steps.
Non-surgical care works best as a plan rather than a collection of attempts. When the plan stops holding the line and the loss matters to your life, that is when a replacement discussion is reasonable, not obligatory.
What an injection can and cannot do
A cortisone injection places anti-inflammatory medication into or around the hip joint, which can calm inflammation and ease pain for a period that varies widely from person to person, often weeks to a few months. Because the hip sits deep in the body, these injections are frequently guided by ultrasound or X-ray so the medication reaches the right spot. When pain relief follows a well-placed injection, it can also help confirm that the hip itself is the source of the pain.
What an injection does not do is rebuild cartilage or reverse arthritis; it manages symptoms rather than changing the underlying joint. Cortisone is usually spaced months apart and used a limited number of times in the same joint, and hyaluronic acid injections, common in the knee, have weaker evidence in the hip. An injection is best understood as a tool that can buy comfort and information, not a cure.
Common worries about staying active
Many people with hip arthritis fear that walking or exercise will wear the joint out faster, and hold still to protect it. For most, the opposite is closer to the truth: regular, low-impact movement helps maintain the muscle that supports the joint, keeps it flexible, and supports sleep, mood, and weight, all of which influence how the hip feels day to day.
A flare of soreness after activity is not usually a sign of damage, and complete rest rarely settles arthritis for long. The useful approach is steady motion within a comfortable range, adjusting the type of activity rather than stopping altogether. What that looks like is individual, and it is worth shaping with your own care team.
When to call rather than wait
A few situations deserve prompt evaluation instead of steady patience: a hip that suddenly cannot bear weight, a hot or swollen joint with fever or chills, night pain that will not settle, or a sharp change after a fall. Call the office about those rather than watching the trend. Emergency symptoms should be handled as emergencies.
What arthritis does to the joint space.
On an X-ray, healthy cartilage shows up as open space between the bones. As arthritis wears that cartilage away, the space can narrow until bone meets bone. Seeing the comparison is often the moment the diagnosis makes sense. Still, the image describes the joint; it does not decide the treatment.
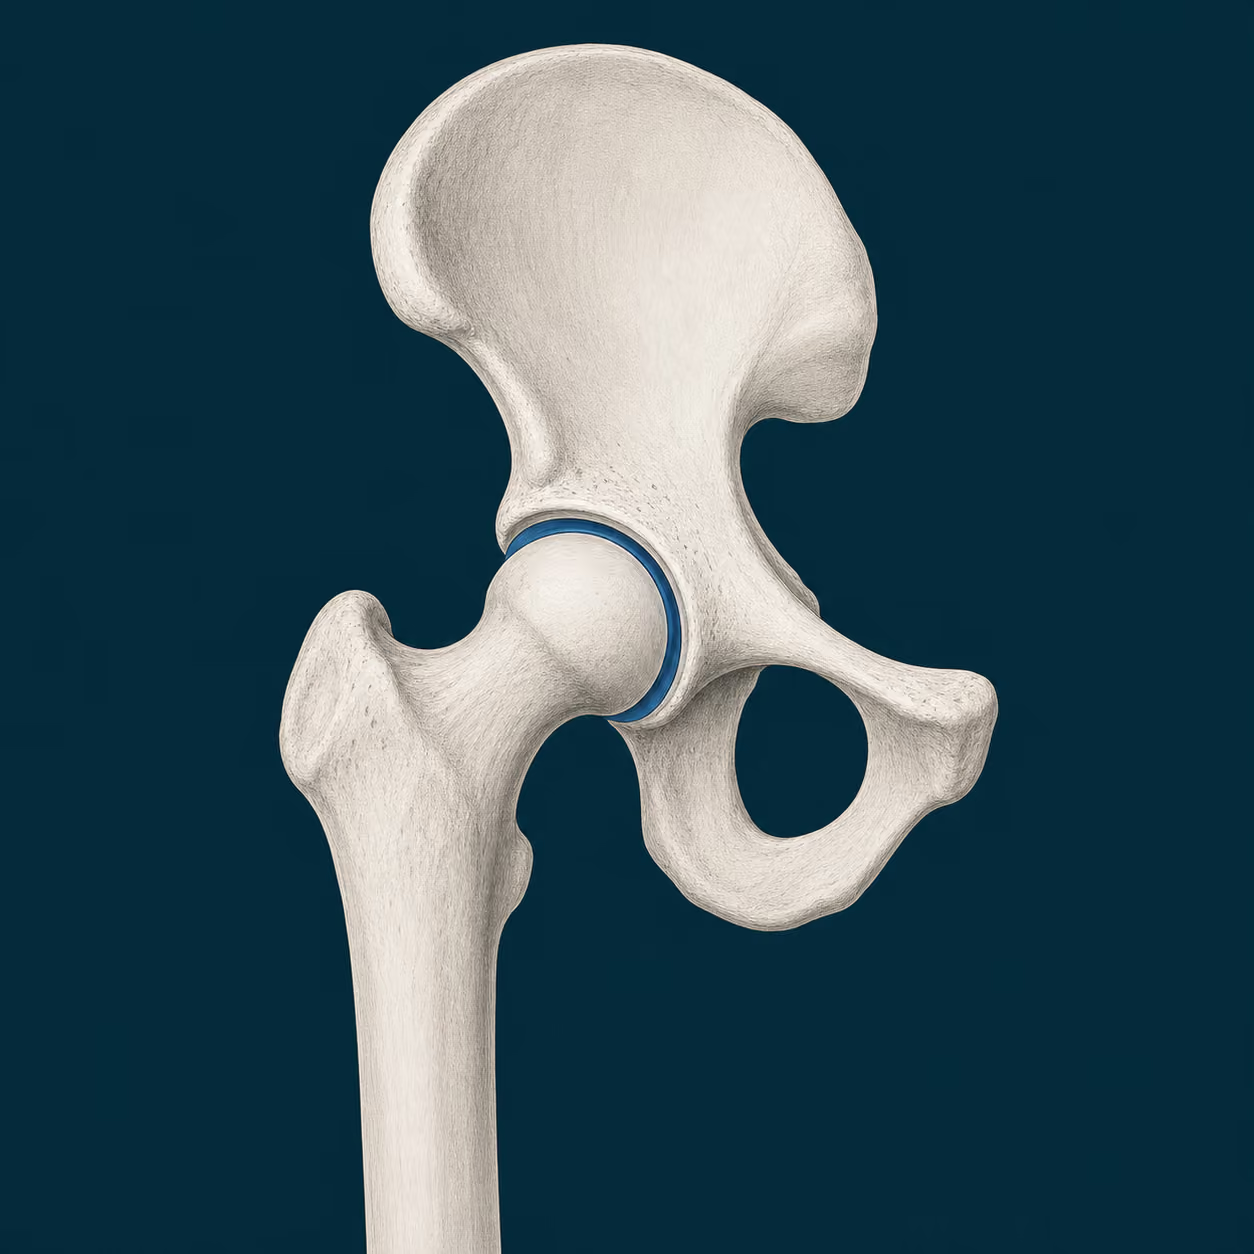
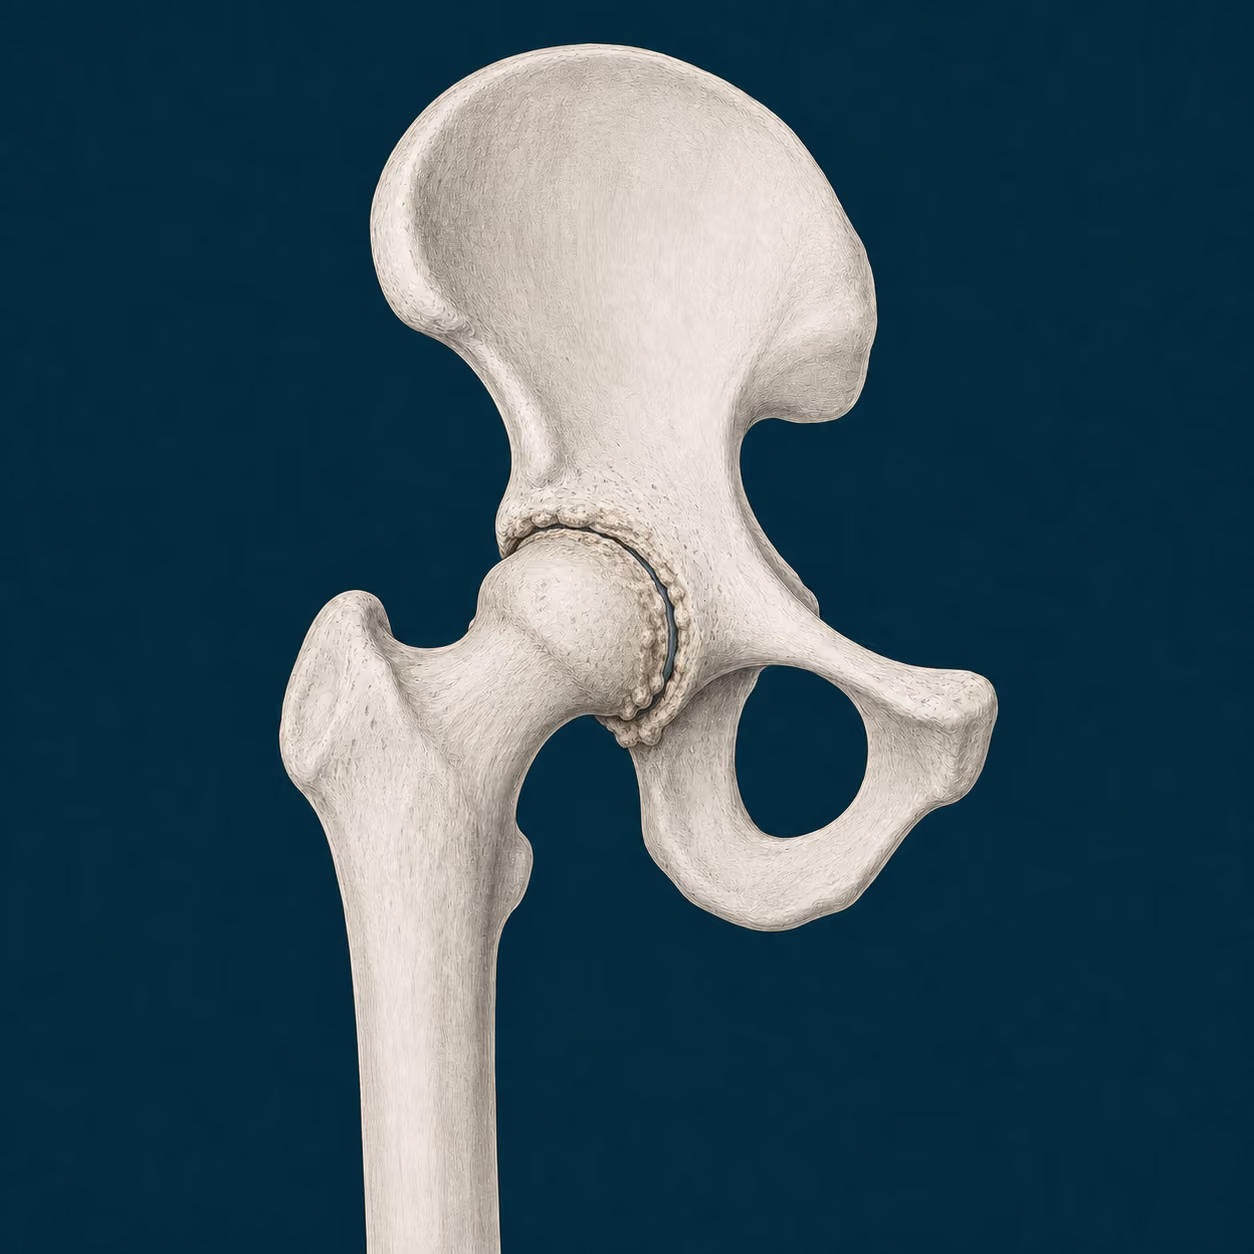
These are educational illustrations, not X-rays of a real person. Your own imaging, and how it matches your symptoms, is what gets read in a consultation.
Where hip pain comes from
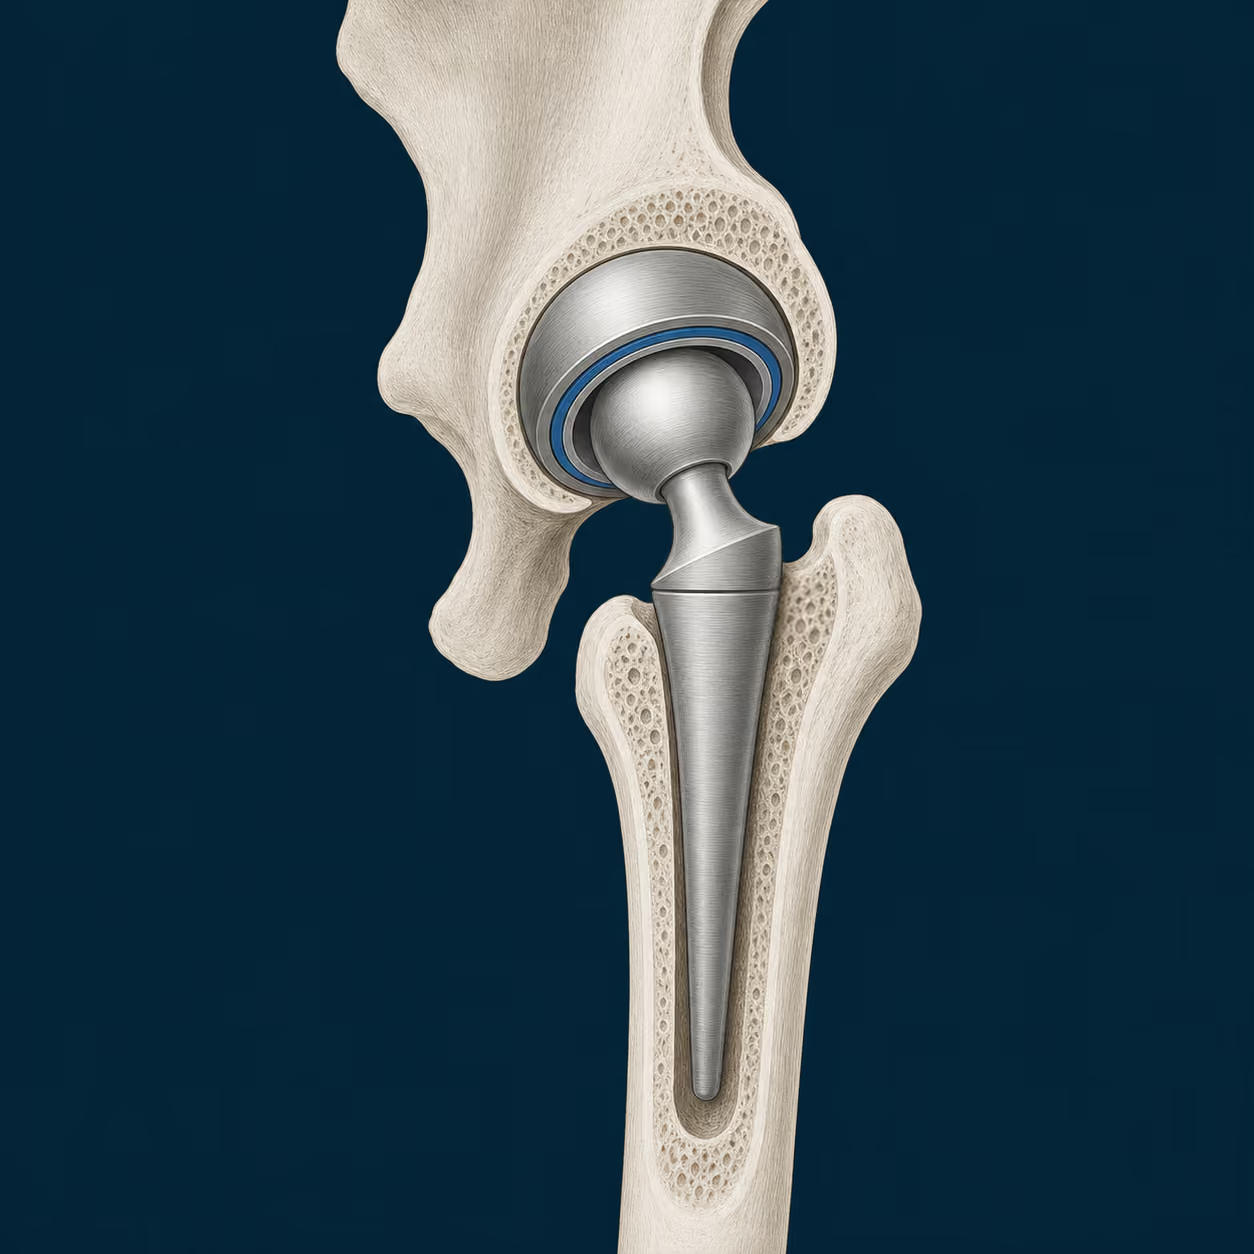
Open the animated walkthrough
General patient-education animation. It explains the topic in broad terms and is not medical advice or a description of your specific plan; bring your questions to a consultation.
Use the consultation to make the decision clearer.
- Is my pain actually coming from the hip joint?
- Which non-surgical options have I genuinely exhausted?
- What does my X-ray show, and what does it not tell us?
- What would I want back if the pain were gone?
- Would an image-guided injection help confirm that my hip is the real source of the pain?
- Given my arthritis, what kinds of activity would you encourage rather than avoid?
- How much relief and for how long would you realistically expect an injection to give me?
Sources and further reading
- Osteoarthritis of the HipAmerican Academy of Orthopaedic Surgeons
- Total Hip ReplacementAmerican Academy of Orthopaedic Surgeons
- Total Hip ReplacementAmerican Association of Hip and Knee Surgeons
- Current Physical Activity GuidelinesU.S. Department of Health and Human Services